
2026 Best New Surgical Robots for Global Buyers?
Choosing new surgical robots for global markets in 2026 requires more than comparing polished demonstrations. Hospitals need evidence that survives daily pressure: a stable robotic arm, clear instrument feedback, reliable imaging, and support when a procedure lasts longer than expected. A system may look impressive in a showroom yet create delays in a busy operating room.
This guide introduces important developments for international buyers, including multi-port, single-port, orthopedic, and image-guided platforms. It examines clinical evidence, regulatory status, cybersecurity, training requirements, maintenance, and long-term ownership costs. These factors can differ sharply between regions. A hospital in Germany may prioritize conformity documentation, while a buyer in Southeast Asia may focus on local service coverage and surgeon education.
Small details matter. Can staff replace a worn instrument without lengthy downtime? Does the supplier provide qualified technicians near the hospital? Are software updates transparent and properly validated? Not every new launch is automatically better. Some claims remain early, limited, or difficult to compare across specialties. That uncertainty deserves attention.
Real operating experience should guide the discussion. Surgeons need practical control, not only advanced specifications. Procurement teams need dependable contracts, measurable training plans, and honest answers about consumables. Patients also deserve consideration, because technology should support safer, more effective care rather than simply increase hospital prestige. This overview helps global buyers assess promising systems carefully, recognize their limitations, and make decisions grounded in evidence, usability, and responsible clinical adoption.
What Defines a New Surgical Robot in 2026
What Defines a New Surgical Robot in 2026
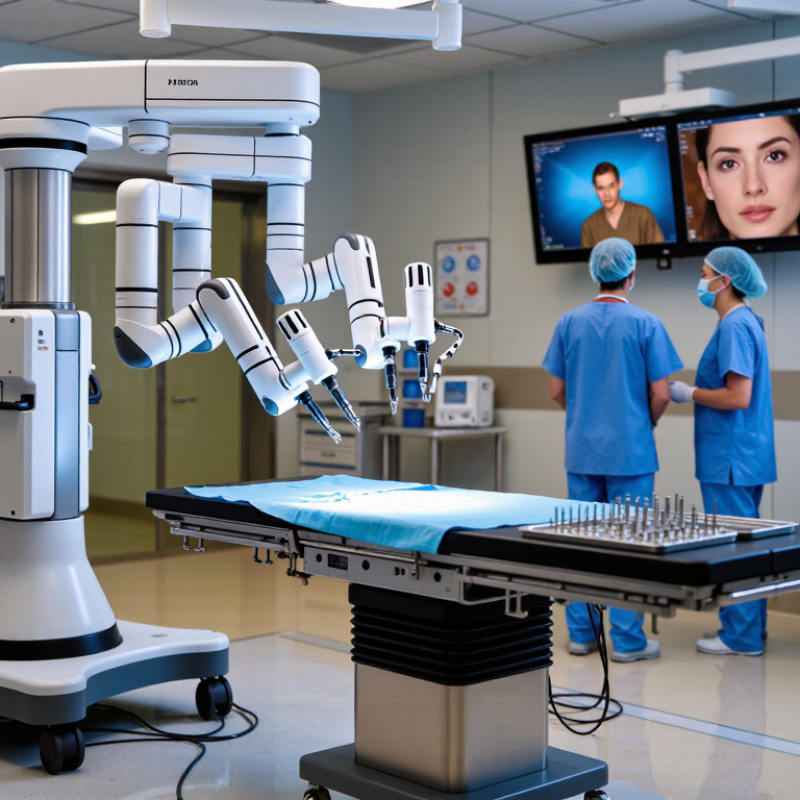
A new surgical robot in 2026 is more than a machine with updated software. It should improve control, visualization, workflow, or patient safety in measurable ways. Buyers should examine published clinical evidence, not impressive demonstrations. A smaller instrument tip means little without reliable tissue handling. Better imaging must also support clearer decisions during complex procedures.
Modern systems increasingly combine robotic arms, three-dimensional imaging, force feedback, and data-guided assistance. However, meaningful innovation still depends on surgeon control. The system should show why it recommends an action and allow immediate human correction. Useful features include stable instrument movement, quick setup, sterile component tracking, and smooth conversion to manual techniques. In a busy operating room, ten saved minutes can matter.
Global buyers also need practical proof beyond the operating table. Ask about local training, maintenance response, software updates, electrical compatibility, and data protection. Hospitals should review regulatory clearance in each target market. Interoperability with imaging and hospital records is equally important. Promises can be polished.
The definition remains imperfect. Some “new” robots mainly refresh older platforms with different interfaces. Others introduce promising automation but lack long-term clinical data. A careful evaluation should include surgeons, nurses, biomedical engineers, and procurement teams. Their daily experience may expose problems that brochures never mention. For instance, a difficult drape change or delayed instrument exchange can reduce the value of advanced technology. Safety evidence, transparent limitations, and dependable service should define novelty in 2026.
2026 Best New Surgical Robots for Global Buyers? – What Defines a New Surgical Robot in 2026
| Evaluation Dimension | What Defines a New Robot in 2026 | Practical Buyer Data | Why It Matters to Global Buyers |
|---|---|---|---|
| Clinical Focus | Designed around a defined clinical workflow rather than marketed only as a general-purpose robotic platform. | Common 2026 focus areas include laparoscopic soft-tissue surgery, orthopaedic procedures, endoluminal intervention, microsurgery, and image-guided navigation. | A focused system can be easier to train, validate, staff, and integrate into existing operating-room procedures. |
| Meaning of “New” | New technology should provide a meaningful improvement in access, precision, workflow, imaging, cost, or clinical capability—not merely a new product label. | Review evidence for at least one measurable improvement: reduced setup time, improved instrument dexterity, fewer staff requirements, better targeting, or lower total ownership cost. | Helps buyers distinguish genuine innovation from incremental hardware refreshes. |
| Surgical Modality | Supports one or more clinically validated modalities, such as laparoscopic, open, orthopaedic, endoscopic, or image-guided surgery. | The modality must match the target procedure volume, instruments, imaging workflow, and hospital infrastructure. | A technically advanced system may still be unsuitable if it does not support the hospital’s highest-priority procedures. |
| Degrees of Freedom | Provides sufficient instrument and camera articulation for the intended procedures, with independent control where clinically useful. | Typical multi-arm soft-tissue platforms may provide approximately 6–8 controlled degrees of freedom per instrument, depending on design. | More articulation can improve access in confined anatomy, but it may also increase complexity, training needs, and cost. |
| Surgeon Control | The surgeon remains responsible for operative decisions and direct control of the procedure in currently deployed mainstream systems. | Look for tremor filtration, motion scaling, clutching, foot controls, ergonomic console design, and clear manual override functions. | Clear control architecture supports patient safety, accountability, and regulatory compliance. |
| Artificial Intelligence | Uses AI primarily for image interpretation, anatomy recognition, workflow assistance, data analysis, or decision support. | AI claims should specify the intended use, training data scope, performance metrics, human oversight, and regulatory status. | AI capability is not equivalent to autonomous surgery; buyers must separate assistive software from independent tissue manipulation. |
| Autonomy Level | Autonomy is described using task-specific functions and defined human supervision, not broad claims of fully autonomous surgery. | Most clinical systems remain surgeon-controlled; automated functions may include camera positioning, image registration, or repetitive assistance. | A precise autonomy description improves risk assessment, training, validation, and procurement decisions. |
| Imaging and Navigation | Combines high-definition visualization with compatible imaging, navigation, or intraoperative guidance when clinically indicated. | Evaluate 2D or 3D visualization, fluorescence capability, image latency, registration accuracy, and compatibility with hospital imaging systems. | Better visualization and navigation can support accurate targeting while reducing unnecessary tissue disruption. |
| Operating-Room Footprint | Uses compact, mobile, modular, or flexible components to reduce interference with staff, anesthesia equipment, and imaging devices. | Confirm room clearance, docking requirements, power supply, floor loading, sterile-field access, and storage needs before purchase. | Space-efficient systems are easier to install in hospitals with smaller or multi-use operating rooms. |
| Setup and Turnaround | Improves docking, instrument exchange, sterile preparation, and procedure turnover through simplified workflow design. | Request independently verified data for setup time, docking time, instrument change time, cleaning, and turnover between cases. | Operating efficiency directly influences daily case capacity and the financial return on capital equipment. |
| Instrument Reuse and Sterilization | Provides clearly documented sterile processing, reprocessing, single-use, and instrument-life requirements. | Compare validated reuse cycles, sterilization method, processing time, disposable components, and local infection-control requirements. | Consumables and reprocessing can materially affect total cost, logistics, and case scheduling. |
| Connectivity and Data | Supports secure data exchange with hospital information systems, imaging archives, analytics tools, and approved remote-support workflows. | Check interoperability standards, cybersecurity controls, encryption, access management, audit logs, data location, and offline operation. | Cross-border buyers must address privacy laws, cybersecurity risk, network reliability, and data sovereignty. |
| Regulatory Readiness | Has a defined intended use and appropriate market authorization or registration for each target country. | Verify approval status, indications, clinical evidence, post-market surveillance, local representative, and import requirements. | A device cleared in one jurisdiction may not be legally marketable or clinically usable in another. |
| Clinical Evidence | Demonstrates safety, performance, usability, and workflow outcomes through appropriate clinical or simulated-use evidence. | Assess study design, sample size, comparator, follow-up period, complication reporting, learning curve, and peer-reviewed publication quality. | Evidence quality is more reliable than promotional claims when comparing emerging systems. |
| Training Requirements | Includes structured surgeon, nursing, biomedical engineering, and sterile-processing training. | Evaluate simulation access, proctoring, credentialing pathway, procedure-specific training, and annual competency requirements. | Training capacity affects adoption speed, patient safety, and the number of clinicians able to use the system. |
| Service and Support | Provides local technical support, preventive maintenance, spare parts, software updates, and response-time commitments. | Compare warranty duration, uptime target, service coverage, spare-parts lead time, remote diagnostics, and escalation procedures. | Support availability is critical in regions where specialist engineers and replacement components are limited. |
| Total Cost of Ownership | Evaluates acquisition, installation, training, service, software, instruments, disposables, sterilization, and facility upgrades together. | Use a five- to seven-year cost model and calculate cost per procedure under realistic annual case volumes. | The purchase price alone does not show whether a surgical robot is economically sustainable. |
| Global Deployment Suitability | Can operate within local infrastructure, workforce, regulation, language, procurement, and supply-chain conditions. | Check voltage and network requirements, local-language manuals, customs classification, consumables availability, and regional service coverage. | A system suitable for a highly resourced hospital may require substantial adaptation in emerging or remote markets. |
Buyer note: Regulatory clearance, indications, performance specifications, pricing, and clinical evidence vary by jurisdiction and product configuration. All figures and claims should be verified with current official documentation before procurement.
Related Posts
-
How to Choose Surgical Robots in 2026?
-

Best Surgical Robots for Efficient Operations in 2026?
-
China Top Robotic Surgery Systems Manufacturers
-
What Are the Benefits of an Advanced Surgery System?
-
Precision Surgery Tips for Enhanced Accuracy and Outcomes?
-

Exploring the Future of Medicine with Robotic Surgical Systems in Minimally Invasive Procedures